
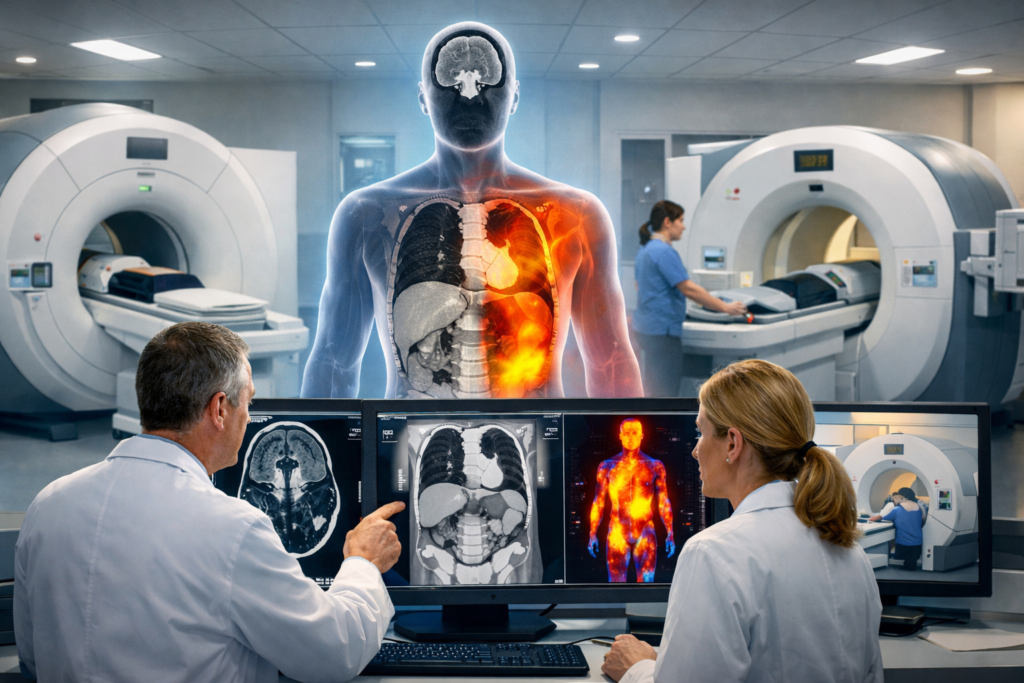
Not so long ago, if a doctor needed to know what was happening inside your body, the options were limited — a basic X-ray, an exploratory surgery, or educated guesswork. Today, a radiologist can map your brain’s blood vessels, detect a cancer smaller than a pea, or watch your heart metabolizing sugar in near real time — all without making a single incision.
The first medical X-ray appeared in 1895. For decades, imaging largely meant detecting fractures or large abnormalities. Today, radiology guides emergency care, cancer treatment, stroke therapy, cardiac management, and preventive medicine. Modern diagnostic imaging has transformed medicine in ways that would have seemed like science fiction to physicians just a few generations ago.
Modern imaging falls into three broad categories: structural imaging — what tissues look like, vascular imaging — how blood flows, and functional imaging — how cells behave metabolically. Here’s a plain-language guide to the big three: MRI/MRA, CT/CTA, and PET scans — what they are, how they work, and why they matter.
MRI and MRA: Magnets and Radio Waves
The MRI — magnetic resonance imaging — is one of the most versatile tools in modern medicine, and it works without a single ray of radiation. An MRI passes an electric current through coiled wires to create a temporary magnetic field in your body. A transmitter and receiver then send and receive radio waves, and a computer uses those signals to construct detailed digital images of whatever area is being scanned. Think of it as a very sophisticated tuning fork: it causes hydrogen atoms in your body’s water molecules to briefly align, then releases them — and the energy they emit on the way back creates the image. Because different tissues relax at different rates, MRI can distinguish gray matter from white matter in the brain, normal from inflamed or cancerous tissue, and ligament from muscle with impressive contrast.
The result is exceptional detail, especially for soft tissue. MRI scans take much clearer pictures of your brain, spinal cord, nerves, muscles, ligaments, and tendons than regular X-rays and CT scans. That’s why your orthopedic surgeon orders one when your knee goes sideways, and why neurologists reach for it when they suspect a stroke or multiple sclerosis.
MRA — magnetic resonance angiography — is MRI’s cousin, using the same magnetic technology but focused specifically on blood vessels. It lets physicians map arteries and veins in remarkable detail, identifying narrowing (stenosis), bulges (aneurysms), or blockages (occlusions) without the need for invasive catheterization. If your doctor suspects a blockage in the blood vessels feeding your brain or kidneys, an MRA can reveal it clearly. A contrast dye is sometimes injected to make vessels stand out even more sharply.
The main trade-offs with MRI are time and noise — scans generally take between 30 to 50 minutes, and the machine produces the kind of clanging racket that makes earplugs standard issue. People with certain metal implants or severe claustrophobia can’t always use it, which is where CT steps in.
CT and CTA: X-Rays, Upgraded
The CT scan — computed tomography — takes the familiar chest X-ray and turns it into something far more powerful. A CT scan takes multiple X-ray images from different angles rotating around the body, separates them by depth then processes them by computer to create cross-sectional views — essentially a detailed 3D picture rather than a flat 2D image. Think of slicing a loaf of bread: instead of seeing only the crust, you can examine every slice.
A CT shows more detail than a standard X-ray and is used to diagnose cancer, heart disease, injuries from trauma, and musculoskeletal disorders — it’s one of the most common imaging tests used today. Emergency departments rely on CT heavily because it’s fast, often completed in 10 to 15 minutes, and can quickly identify life-threatening conditions like internal bleeding or pulmonary embolism.
CTA — CT angiography — adds an injected contrast dye to the mix, allowing physicians to see blood vessels with high clarity. Contrasting agents help show various structures of the body more clearly, making CTA the go-to test for evaluating coronary arteries, aortic aneurysms, and vascular disease throughout the body. Unlike MRA, it’s faster and more widely available, though it does involve a dose of radiation — something physicians weigh carefully against the diagnostic benefit.
PET Scan: When Function Matters More Than Form
If MRI and CT show you the structure of the body, the PET scan — positron emission tomography — shows you what’s happening inside it. This is a fundamentally different question, and the technology reflects that.
A PET scan is used to see metabolism and chemical activity within your body. It can detect abnormal changes before structural changes occur — meaning it can detect cancer before a tumor is large enough to be seen on a CT or MRI. That’s a remarkable capability. The scan works by injecting a small amount of a radioactive tracer — most commonly a form of glucose — into your bloodstream. Diseased cells, particularly cancer cells, absorb more of the radiotracer than healthy ones do. Active cells consume glucose. Cancer cells, inflamed tissue, and active brain regions often use more glucose than surrounding tissue. These are called “hot spots,” and the PET scanner detects this radiation to produce images of affected tissue.
Beyond cancer, PET scans are invaluable in cardiology — showing whether heart muscle is still alive after a heart attack — and in neurology, helping diagnose Alzheimer’s disease, epilepsy, and brain tumors by revealing abnormal patterns of brain activity.
The trade-off is resolution. The image resolution of nuclear medicine images may not be as high as that of CT or MRI, which is why PET is rarely used alone today. Combined PET/CT scanners perform almost all PET scans today , marrying metabolic information with anatomical precision. Hybrid PET/MRI scanners are also emerging though not yet in widespread use. They are particularly valuable for soft-tissue cancers of the brain, liver, and pelvis.
How They Compare — and Why It Matters
The simplest way to think about these three technologies is this: CT shows shape and structure quickly, with emphasis on bone and dense tissue; MRI shows soft tissue in extraordinary detail without radiation; and PET shows function and cellular activity that neither of the others can see directly.
A patient with suspected cancer might undergo a CT scan to identify the location of a mass, followed by a PET to determine its metabolic activity, and then an MRI to map its relationship to critical soft tissues. Used together, these tools give physicians a picture of disease that is more complete than any single test could provide.
The value to modern medicine is difficult to overstate. These technologies allow doctors to diagnose conditions earlier, stage cancers more accurately, guide surgical planning, and monitor how well treatments are working — all without exploratory surgery. Survival rates for many cancers have improved substantially in part because imaging lets us find disease when it’s still manageable.
The era when medicine was largely guesswork about what lay beneath the skin is over. Today, radiologists are, in a very real sense, reading the body like an open book.
Illustration generated by author using ChatGPT.
Sources:
UNC Health Appalachian — MRI, CT, and PET Scan Comparison: https://www.unchealthappalachian.org/blog/2024/comparing-mri-ct-and-pet-scans-how-they-work-and-when-theyre-use/
WashU Mallinckrodt Institute of Radiology — Differences Between CT, MRI, and PET: https://www.mir.wustl.edu/do-you-know-the-differences-between-a-ct-mri-and-pet-scan/
Cleveland Clinic — PET Scan Overview: https://my.clevelandclinic.org/health/diagnostics/10123-pet-scan
RadiologyInfo.org — PET/CT: https://www.radiologyinfo.org/en/info/pet
Open MedScience — CT, MRI, and PET Differences: https://openmedscience.com/ct-mri-and-pet-scanners-unravelling-the-differences-in-modern-medical-imaging/
Healthline — MRI vs. PET Scan: https://www.healthline.com/health/mri-vs-pet-scan
Revere Health — MRI, CT, and PET Explained: https://reverehealth.com/live-better/mri-ct-pet/





The Price Tag Mystery: Why Nobody Really Knows What Healthcare Costs in America
By John Turley
On January 29, 2026
In Commentary, Medicine, Politics
Imagine walking into a store where nothing has a price tag. When you get to the register, the cashier scans your items and tells you the total—but that total is different for every customer. Your neighbor might pay $50 for the same items that cost you $200. The store won’t tell you why, and you won’t find out until after you’ve already “bought” everything.
Welcome to American healthcare, where the simple question “how much does this cost?” has no simple answer.
You might think I’m exaggerating, but the evidence suggests otherwise. Research published in late 2023 by PatientRightsAdvocate.org found that prices for the same medical procedure can vary by more than 10 times within a single hospital depending on which insurance plan you have, and by as much as 33 times across different hospitals. A knee replacement that costs around $23,170 in Baltimore might run $58,193 in New York. An emergency department visit that one facility charges $486 for might cost $3,549 at another hospital for the identical service.
The fundamental problem is that hospitals and doctors don’t have one price for their services. They have dozens, sometimes hundreds, of different prices for the exact same procedure depending on who’s paying. This bizarre system evolved because most healthcare in America isn’t a simple transaction between patient and provider—there’s a third party in the middle called an insurance company, and that changes everything.
The Fiction of Chargemaster Prices
A hospital chargemaster is essentially the hospital’s internal price list—a massive catalog that assigns a dollar amount to every service, supply, test, medication, and procedure the hospital can bill for, from an aspirin to a complex surgery. These listed prices are usually very high and are not what most patients actually pay; instead, the chargemaster functions as a starting point for negotiations with insurers and government programs like Medicare and Medicaid, which typically pay much lower, pre-set rates. What an individual patient ultimately pays depends on several factors layered on top of the chargemaster price. Think of them like the manufacturer’s suggested retail price on a car: technically real, but nobody pays them.
A hospital might list an MRI at $3,000 or a blood test at $500. But then insurance companies come in. They represent thousands or millions of potential patients, which gives them serious bargaining power. They negotiate with hospitals along these lines: “We’ll send you lots of patients, but only if you give us a discount.” So, the hospital agrees to accept much less—maybe they’ll take $1,200 for that $3,000 MRI or $150 for the blood test. This discounted amount is called the “negotiated rate,” and it’s what the insurance company will really pay.
Here’s where it gets messy: every insurance company negotiates its own rates with every hospital. Blue Cross might negotiate one price, Aetna a different price, UnitedHealthcare yet another. The same exact MRI at the same hospital might be $1,200 for one insurer’s customers and $1,800 for another’s. And these negotiated rates have traditionally been kept secret—treated like confidential business information that gives each party a competitive advantage.
The Write-Off Game
What happens to that difference between the chargemaster price and the negotiated rate? The hospital “writes it off.” That’s accounting language for “we accept that we’re not getting paid this money, and we’re taking it off the books.” If the hospital charged $3,000 but agreed to accept $1,200, they write off $1,800. This isn’t lost money in the normal sense—they never expected to collect it in the first place. The chargemaster prices are inflated specifically because everyone knows discounts are coming. Some hospitals now post “discounted cash prices” that are often far below chargemaster and sometimes even below some negotiated rates. These are sometimes, though not always, offered to uninsured patients, generally referred to as self-pay. There can be a catch—some hospitals require lump-sum payment of the total bill to qualify for the lower price.
According to the American Hospital Association, U.S. hospitals collectively plan to write off approximately $760 billion in billed charges in 2025 across all categories of write-offs. That’s not a typo—$760 billion. These write-offs happen in several different situations. The most common are contractual write-offs, where the provider has agreed to accept less than their list price from insurance companies.
Hospitals have far more write-offs than just contractual. They also write off money for charity care—treating patients who can’t afford to pay anything, and they write off bad debt when patients could pay but don’t. They write off small balances that aren’t worth the administrative cost of collection, and they write off amounts related to various billing errors, denied claims, and coverage disputes. Healthcare providers typically adjust about 10 to 12 percent of their gross revenue due to these various write-offs and claim adjustments.
Why Such Wild Variation?
Even with all these negotiated discounts built into the system, the prices still vary enormously. A 2024 study from the Baker Institute found that for emergency department visits, the price charged by hospitals in the top 10% can be three to seven times higher than the hospitals in the bottom 10% for the identical procedure. Research published in Health Affairs Scholar in early 2025 found that even after adjusting for differences between insurers and procedures, the top 25% of prices across all states is 48 percent higher than the bottom 25% of prices for inpatient services.
Several factors drive this variation. Hospitals in areas with less competition can charge more because insurers have fewer alternatives for negotiation. Prestigious hospitals can demand higher rates because insurers want them in their networks to attract customers. Some insurance companies have more bargaining power than others based on their market share. There’s no central authority setting prices—it’s all private negotiations, hospital by hospital, insurer by insurer, procedure by procedure.
For patients, this creates a nightmare scenario. Even if you have insurance, you usually have no idea what you’ll pay until after you’ve received care. Your out-of-pocket costs depend on your deductible (the amount you pay before insurance kicks in), your copay or coinsurance (your share after insurance starts paying), and whether the negotiated rate between your specific insurance and that specific hospital is high or low. Two people with different insurance plans getting the same procedure at the same hospital on the same day can end up with drastically different bills.
Research using new transparency data confirms this isn’t just anecdotal. A study from early 2025 found that for something as routine as a common office visit, mean prices ranged from $82 with Aetna to $115 with UnitedHealth. Within individual insurance companies, the price of the top 25% of office visits was 20 to 50 percent higher than the bottom 25%, meaning even within one insurer’s network, where you go or where you live makes a huge difference.
The Government Steps In
The federal government finally said “enough” and started requiring transparency. Since 2021, hospitals must post their prices online, including what they’ve negotiated with each insurance company. The Centers for Medicare and Medicaid Services (CMS) strengthened these requirements in 2024, mandating standardized formats and increasing enforcement. Health insurance plans face similar requirements to disclose their negotiated rates.
The theory was straightforward: if patients could see prices ahead of time, they could shop around, which would force prices down through competition. CMS estimated this could save as much as $80 billion by 2025. The idea seemed sound—transparency works in other markets, so why not healthcare?
In practice, it’s been messy. A Government Accountability Office (GAO) report from October 2024 found that while hospitals are posting data, stakeholders like health plans and employers have raised serious concerns about data quality. They’ve encountered inconsistent file formats, extremely complex pricing structures, and data that appears to be incomplete or possibly inaccurate. Even when hospitals post the required information, it’s often so convoluted that comparing prices across facilities becomes nearly impossible for average consumers.
An Office of Inspector General report from November 2024 found that not all selected hospitals were complying with the transparency requirements in the first place. And CMS still doesn’t have robust mechanisms to verify whether the data being posted is accurate and complete. The GAO recommended that CMS assess whether hospital pricing data are sufficiently complete and accurate to be usable, and to assess if additional enforcement if needed.
Imagine trying to comparison shop when one store lists prices in dollars, another in euros, and a third uses a proprietary currency they invented. That’s roughly where we are with healthcare price data—technically available, but practically unusable for most people trying to make informed decisions.
The Trump administration in 2025 signed a new executive order aimed at strengthening enforcement of price transparency rules and directing agencies to standardize and make hospital and insurer pricing information more accessible; this action built on rather than reduced the earlier requirements. Hopefully this will improve the ability of patients to access real costs, but it is my opinion that the industry will continue to resist full and open compliance.
The Limits of Shopping for Healthcare
There’s also a deeper philosophical problem: for healthcare to work like a normal market where price transparency drives competition, patients would need to be able to shop around based on price. That could work for scheduled procedures like knee replacements, colonoscopies, or elective surgeries. You have time to research, compare, and choose.
But it doesn’t work at all when you’re having a heart attack, or your child breaks their arm. You go to the nearest hospital, period. You’re not calling around asking about prices while someone’s having a medical emergency. Even for non-emergencies, choosing based on price assumes equal quality across providers, which isn’t always true and is even harder to assess than price itself.
A study on price transparency tools found mixed results on whether they truly reduce spending. Some research shows modest savings when people use price comparison tools for shoppable services like imaging and lab work. But utilization of these tools remains low, and for many healthcare encounters, price shopping simply isn’t practical or appropriate.
Who Really Knows?
So, who truly understands what things cost in this system? Hospital administrators know what different insurers pay them for specific procedures, but that knowledge is limited to their facility. They don’t necessarily know what other hospitals charge. Insurance company executives know what they’ve negotiated with various hospitals in their network, but they haven’t historically shared meaningful price information with their customers in advance. And they don’t know what their competitors have negotiated.
Patients, caught in the middle, often find out their costs only when they receive a bill weeks after treatment. By that point, the care has been delivered, and the financial damage is done. Recent surveys suggest that surprise medical bills remain a significant problem, with many patients receiving unexpected charges from out-of-network providers they didn’t choose or even know were involved in their care.
The people who are starting to get a comprehensive view are researchers and policymakers analyzing the newly available transparency data. Studies published in 2024 and 2025 using these data have given us unprecedented visibility into pricing patterns and variation. But this is aggregate, statistical knowledge—it helps us understand the system but doesn’t necessarily help individual patients figure out what they’ll pay for a specific procedure.
Where We Stand
The transparency regulations represent a genuine attempt to inject some market discipline into healthcare pricing. Making negotiated rates public breaks down the information asymmetry that has allowed prices to vary so wildly. In theory, if patients and employers can see that Hospital A charges twice what Hospital B does for the same procedure, competitive pressure should push prices toward the lower end.
There’s some early evidence this might be working. A study of children’s hospitals found that price variation for common imaging procedures decreased by about 19 percent between 2023 and 2024, though overall prices continued rising. Whether this trend will continue and expand to other types of facilities remains to be seen. I am concerned that rather than lowering overall prices it may cause hospitals at the lower end to raise their prices closer to those at the higher end.
Significant obstacles remain. The data quality issues need resolution before the information becomes truly usable. Many patients lack either the time, expertise, or practical ability to shop based on price. And the fundamental structure of American healthcare—with its complex interplay of providers, insurers, pharmacy benefit managers, and government programs—means that even perfect price transparency won’t create a simple, straightforward market.
So, to return to the original question: does anyone truly know the cost of medical care in the United States? In an aggregate sense, researchers and policymakers are starting to understand the patterns thanks to transparency requirements. The data are revealing just how variable and opaque pricing has been. But as a practical matter for individual patients trying to figure out what they’ll pay for needed care, not really. The information is becoming available but remains largely inaccessible or incomprehensible for ordinary people trying to make informed healthcare decisions.
The $760 billion in annual write-offs tells you everything you need to know: the posted prices are largely fictional, the negotiated prices vary wildly, and the system has evolved to be so complex that even the people operating within it struggle to understand the full picture. We’re making progress toward transparency, but we’re a long way from a healthcare system where patients can confidently get the answer to the simple question: “How much will this cost?”
A closing thought: All of this could be solved by development of a single-payer healthcare system such as I proposed in my previous post America’s Healthcare Paradox: Why We Pay Double and Get Less.